
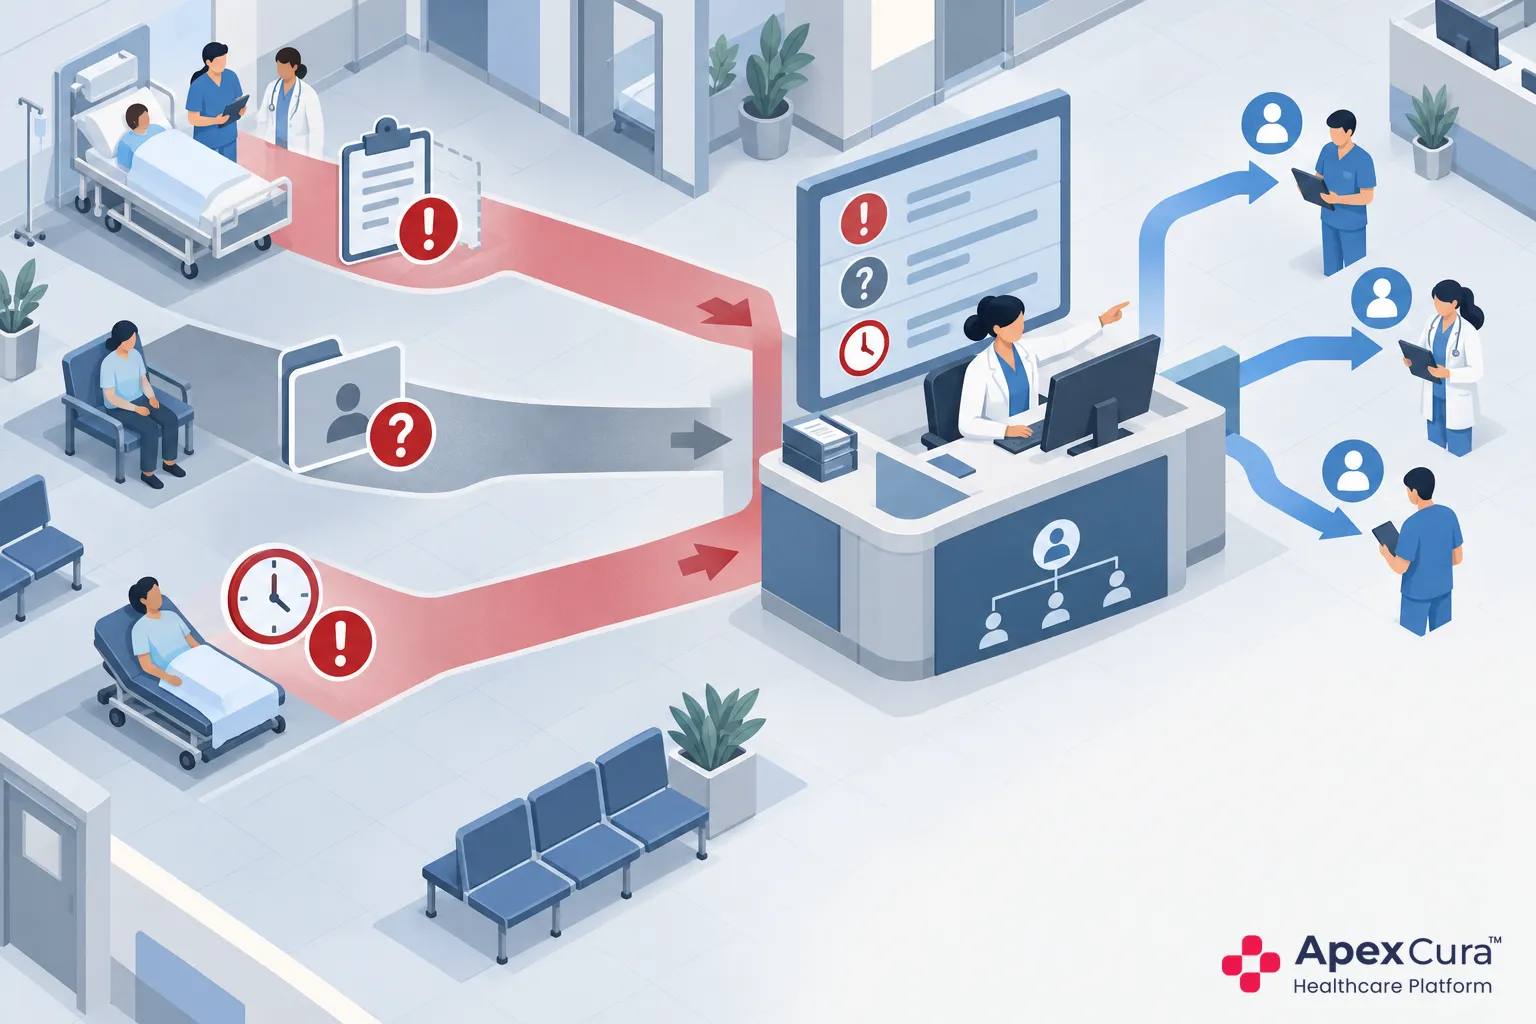
A Complete Admission Recommendation Creates a Clear Counselling Handover
Admission, Surgery and Revisit Recommendations Need Separate Classification
Admission, surgery and revisit advice lead to different actions and should not be placed under one generic follow-up label. An admission recommendation may need immediate counselling about the next hospital step. A planned surgery may require medical and cost clarification. A revisit recommendation needs a future appointment or confirmation that the patient returned. Separate classification gives the counselling team the right starting point and keeps revisit patients out of the OPD-to-IP conversion denominator. The doctor remains responsible for the clinical recommendation; the tracking process records what happens after it.
Admission Advice Should Be Recorded Before the Patient Leaves the OPD
The handover begins when the doctor records that admission is advised. Capturing it while the OPD visit is active reduces dependence on later memory or manual list preparation. If the recommendation changes after clinical review, the treating team should update it. Timely capture gives the counselling desk a reliable work item and establishes when the hospital should begin the next operational action. The record should carry the recommendation time and source so teams can verify that the handover began from authorised doctor advice.
Required Patient, Doctor and Service Details Should Be Complete
The counselling team needs enough verified information to identify the patient, understand the advised service and reach the right clinical team when clarification is needed. At minimum, the case should link the patient, doctor, speciality, branch, consultation and recommendation. Contact details and relevant hospital context should come from authorised systems. An incomplete case should remain visible for correction rather than being silently ignored. The goal is a usable handover, not the collection of unnecessary patient data. A completeness rule can flag missing contact, speciality, branch or advised-service details before the case reaches the counselling worklist during the initial handover review.
Each Admission Case Should Receive an Owner Before Handover
A complete case still needs responsibility. The hospital should assign a counsellor or team using a defined rule and show whether the assignment was accepted. If the patient is moving directly from consultation to a counselling desk, the digital owner should match the operational handover. If the counsellor is unavailable, the case should return to a visible queue for reassignment. This prevents a recommendation from appearing processed merely because it was entered into the system. The system should record assignment time, responsible counsellor and acceptance status so supervisors can identify cases that were routed but not received during daily review.
Status Tracking Identifies Unassigned, Unattended and Overdue Admission Cases
Counselling Status Shows Whether the Conversation Is Awaiting, Started or Completed
A simple current status tells the team what has happened without reading every note. Awaiting counselling means the case is assigned but the first conversation has not started. Started means the team has spoken with the patient but information or a decision is still pending. Completed means the required counselling has been delivered, although the patient may still need time to decide. The status should guide the next action: a started case may need a doctor clarification, estimate or family discussion, while a completed case may need only a decision check at the time agreed with the patient. Hospitals should define these terms consistently so the exception views below are reliable.
Unassigned Cases Have No Counsellor Responsible for Action
An unassigned case is a recommendation that entered the workflow but has no responsible counsellor or team. Common causes include incorrect routing, unavailable staff or missing service mapping. Supervisors should review this list frequently because no patient action can be expected until ownership is clear. Assignment ageing can show how long recommendations wait before a team receives them. The corrective action is operational: fix the routing or allocate capacity, rather than recording the patient as non-responsive. A daily unassigned queue should show the service, branch, recommendation age and routing failure so supervisors can correct the appropriate rule before another shift.
Unattended Cases Have Not Received the First Counselling Conversation
An attended status should mean that the initial counselling conversation genuinely started, not merely that someone opened the record. The hospital may define evidence such as an in-person handover, a completed call or documented first discussion. Cases that remain unattended after assignment need review. The counsellor may be handling excess workload, the patient may have left the OPD or the contact information may need correction. Each cause requires a different response and should not be hidden under one pending label. For example, opening the patient record or sending it to another desk should not count as a completed first counselling action.
Overdue Cases Have Not Reached Their Expected Initial Counselling Action
Hospitals should define a suitable initial-action expectation for each recommendation type and service. An immediate admission recommendation may need same-visit counselling, while an elective admission may follow a different timetable. A case becomes overdue when the expected first action has not happened and no valid reason is recorded. This definition keeps early handover delays separate from later follow-ups for patients who have already received counselling and remain undecided. The overdue view should show the expected action time, elapsed delay and assigned owner. It should also show whether the patient is still in the OPD or has already left. Supervisors can examine these fields during the daily exception review.
Discuss how Apex Cura can help your hospital identify incomplete, unassigned and delayed admission counselling handovers.
Discuss Admission TrackingApex Cura Keeps Admission Recommendations Visible Until the Patient Decides
Exception Views Separate Unassigned, Unattended and Overdue Cases
Apex Cura can organise admission recommendations by assignment and counselling status so hospital teams can distinguish an incomplete handover from a normal pending decision. Supervisors can review unassigned cases, recommendations without an initial counselling action and cases that exceeded the expected time. This exception view directs attention to operational gaps instead of presenting every open case in one long list. Teams still need to verify the reason and complete the appropriate action. Each list should show why the case entered the exception, how long it has remained there and which supervisor must coordinate the correction before the next operating shift.
Alerts Bring Delayed Admission Handoffs to the Responsible Team
When an admission handover remains incomplete, reminders or escalation can bring it back to the responsible counsellor or supervisor. The alert should state what is missing—assignment, first counselling action or required case information—so the team knows how to respond. It should not automatically classify the patient as lost or send repeated messages without review. The hospital defines the timing and escalation rule according to the service and urgency of the operational handover. Escalation should move from the assigned counsellor to the supervisor after the hospital-defined limit, while retaining every reminder and response in the case history until ownership is confirmed.
Decision History Records Proceeding, Postponed, Declined and No-Response Outcomes
After the initial handover is completed, the same case can retain counselling activity and the patient’s eventual decision. Proceeding, pending, postponed and declined outcomes should remain linked to the original doctor advice. This allows the Patient Financial Counselling workflow to show both early handover exceptions and later outcomes without losing the audit trail. Detailed pending follow-ups should follow their own plan after initial counselling, while the admission recommendation remains the common reference point. A dated timeline should preserve initial counselling, later follow-ups and the final verified reason so management can review the complete recommendation journey during later management review meetings.
The final status should reflect the patient’s actual decision. Proceeding may lead to admission, surgery scheduling or a planned revisit. Postponed should include the expected review point when known. Declined should record the verified reason without turning the note into a judgement about the patient. No response should be used only after the hospital completes its defined contact effort. Consistent outcome recording protects patient choice and avoids inflated conversion claims.
Conclusion
Doctor recommendation tracking starts by recording admission, surgery and revisit advice as separate cases during the OPD visit. Admission recommendation tracking should expose the early operational gaps that occur between doctor advice and the first counselling action. A complete recommendation needs verified context, clear ownership and a meaningful status. Hospitals should review unassigned, unattended and overdue cases separately because each requires a different correction. Once the handover is complete, the recommendation can remain connected to later counselling and the patient’s final decision. This creates continuity without confusing a hospital-side delay with a patient who has already received counselling and needs time.







