Understanding the Complete Hospital Patient Acquisition Funnel
Generating Patient Enquiries Across Marketing Channels
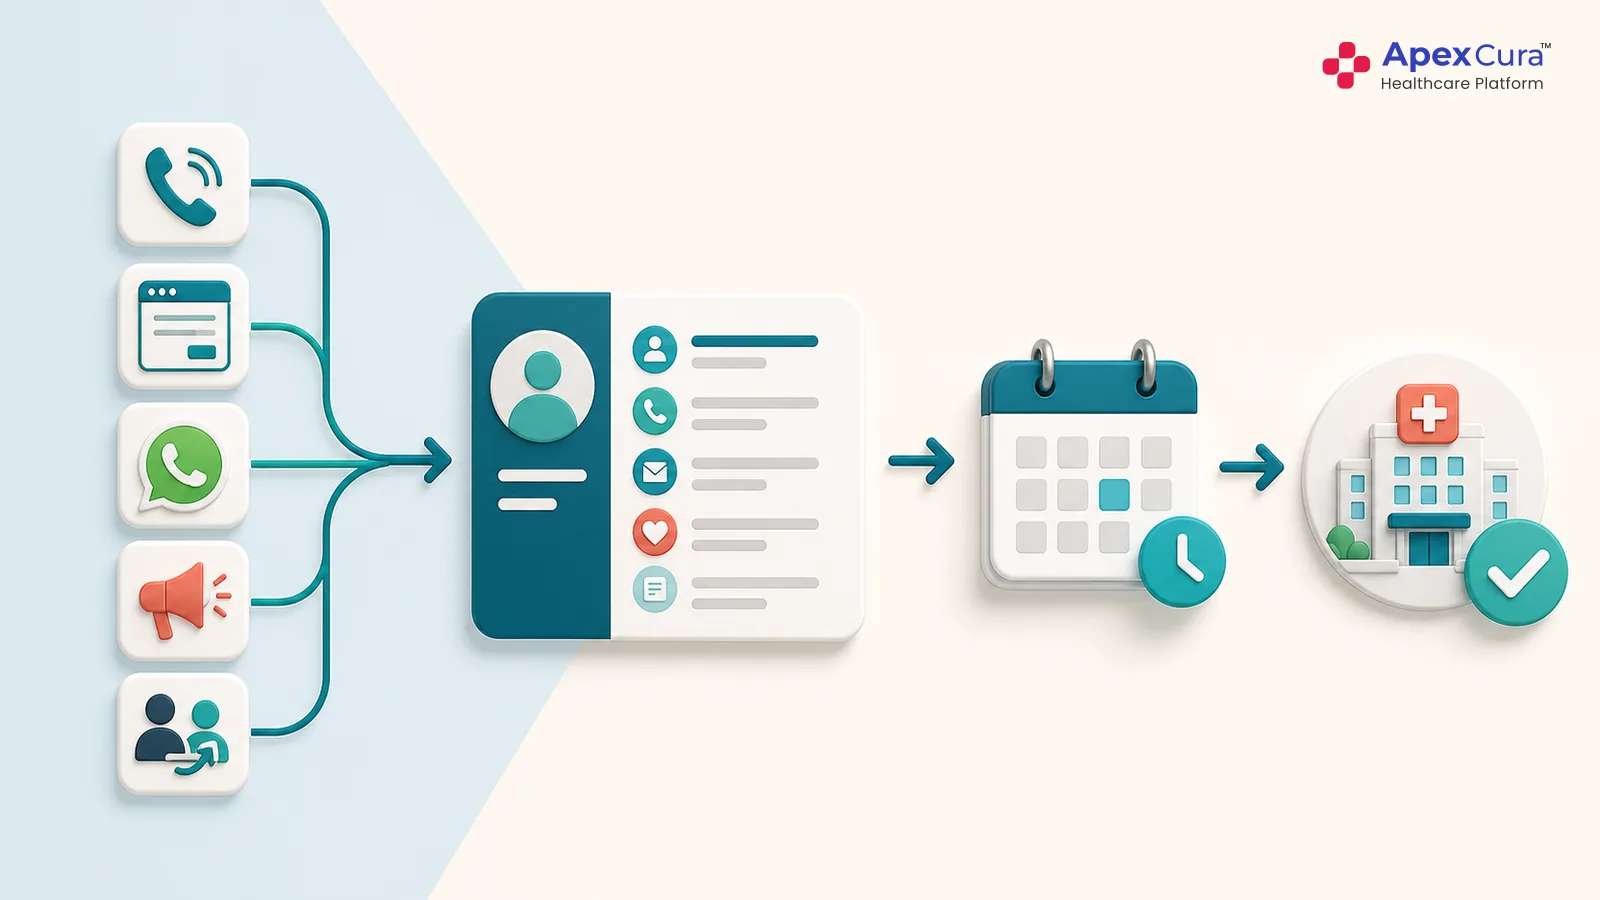
Hospitals generate patient demand through Google, Meta, search visibility, websites, health camps, referrals, calls and WhatsApp. Each channel reaches patients at a different stage of need. A search enquiry may involve an immediate doctor requirement. A campaign response may need more information before booking.
Hospitals should capture the source and campaign when the enquiry first arrives. The record should also include the patient’s service, speciality and preferred location. Reliable capture gives marketing and operations a shared starting point. It also prevents valid enquiries from remaining inside advertising platforms, call logs or individual messages without an assigned follow-up.
Turning Marketing Enquiries Into Booked Appointments
Marketing creates interest, but hospital operations convert that interest into an appointment. The contact centre or counsellor must respond, understand the requirement and provide a suitable doctor or service option.
Response: Staff need current schedules, branch information and a clear follow-up process. A patient may not confirm during the first call, so the next action should be recorded.
Information: Delayed responses, unavailable information and unclear ownership can reduce conversion even when campaigns generate good enquiries. Hospitals should therefore measure the journey from enquiry received to patient contacted and appointment booked.
Follow-up: This shows whether the acquisition problem begins with marketing quality or operational execution.
Extending Patient Acquisition From Appointment to Admission
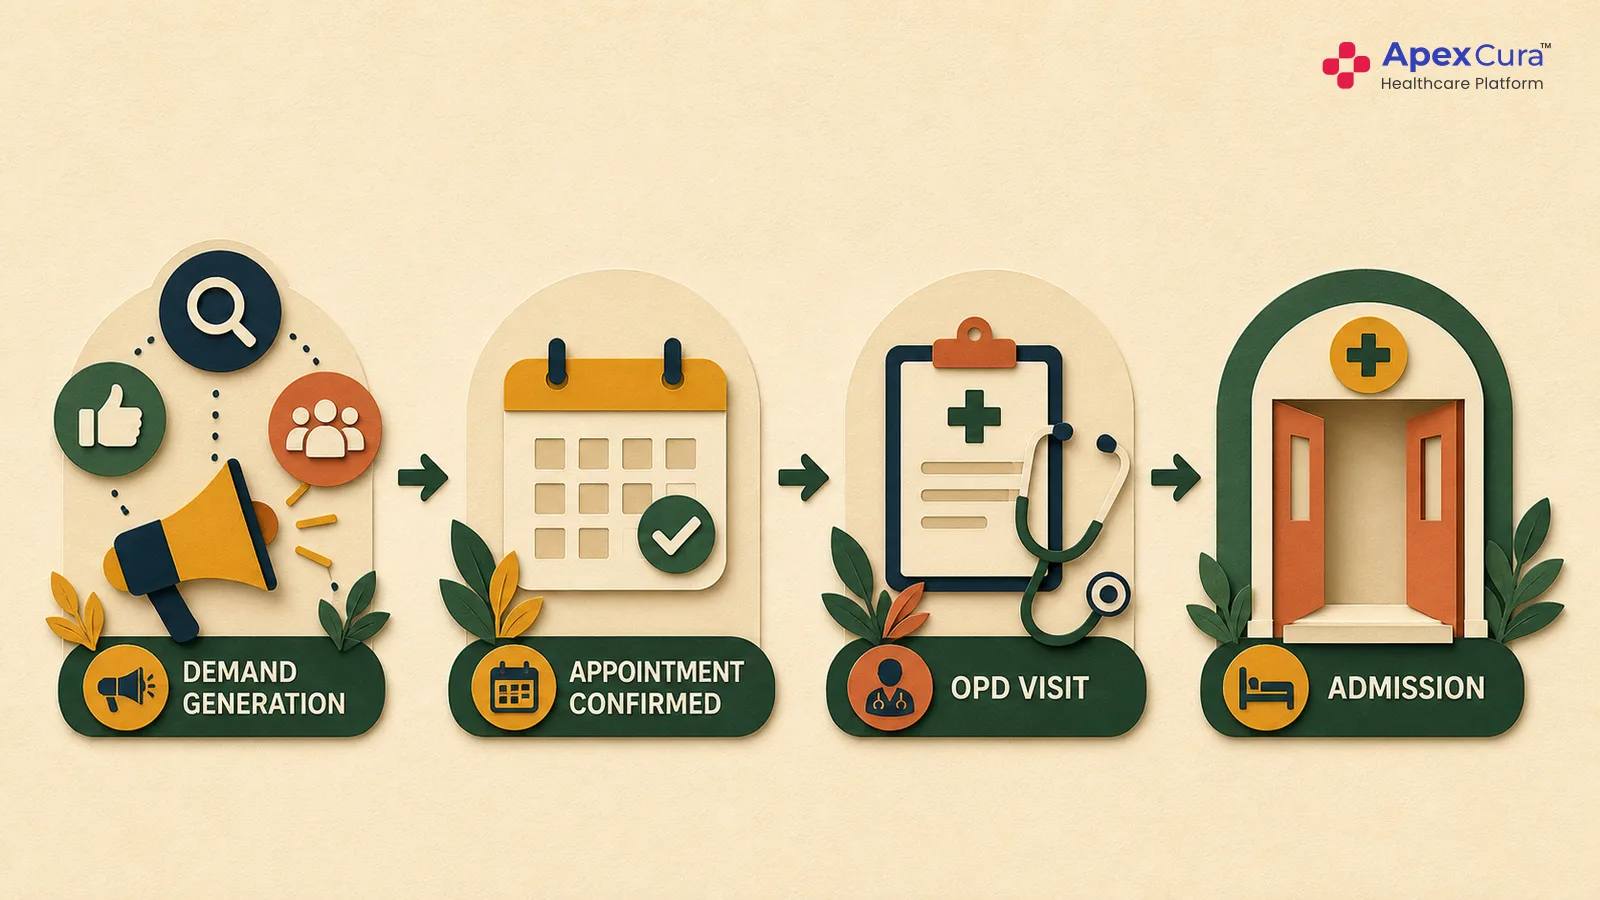
A booked appointment is an important step, but it is not the final hospital outcome. The patient must arrive, complete the OPD visit and follow the advised care plan. Depending on the requirement, the journey may continue to diagnostics, a procedure or admission.
Hospitals should connect these stages where reliable patient matching is available. This broader funnel shows which enquiries create actual care activity and revenue.
It also identifies patients who book but do not visit or attend OPD without completing the advised next step. Measuring the complete journey gives leadership a more realistic view of acquisition performance.
Where Hospitals Lose Patients During Acquisition
Losing Enquiries Between Marketing and the Contact Centre
An advertisement or website may generate an enquiry, but the record may not reach the contact centre correctly. Forms can fail, call details may remain in a separate system and source information can disappear during manual transfer.
- Leads may also arrive after working hours without a defined owner.
- Hospitals should regularly compare channel records with CRM capture.
- They should check whether every connected source creates a usable enquiry with the right time and campaign.
- Exceptions need a visible queue for correction.
- Closing this first gap ensures that marketing demand becomes actionable work instead of remaining only as clicks, calls or platform reports.
Losing Patients Between Enquiry and Appointment
Patients often drop out when the hospital responds late or cannot provide clear next steps. Doctor schedules may be unavailable, calls may remain unanswered or repeated follow-ups may not happen. A patient can also receive different information from separate teams. Every enquiry should have an owner, response expectation and recorded outcome. Staff need enough information to offer an appointment or explain when they will return with an answer. Supervisors should monitor unattended and ageing leads. These controls do not guarantee that every patient will book. They ensure that genuine interest is not lost because of an avoidable internal delay or incomplete handover.
Losing Patients Between Appointment, OPD and Admission
Patients can still leave the acquisition funnel after booking. Some miss the appointment, while others visit OPD but do not complete the recommended test, procedure or admission.
No-shows: The reason may involve timing, cost, clinical choice, counselling or lack of follow-up. Appointment, HIMS and CRM data should show the latest available stage.
Counselling: Teams can then follow up where it is appropriate and useful. Hospitals should record no-shows and non-conversion reasons instead of leaving records open indefinitely.
Closure: This helps management understand whether patients are being lost before the visit, during hospital operations or after the clinical recommendation.
Connect marketing enquiries with appointments, OPD visits, admissions and revenue outcomes.
Explore Apex Healthcare CRMHow Hospitals Improve Enquiry Conversion Rates
Measure Conversion Stage by Stage, Not as One Final Rate
Hospital enquiry conversion is often reported as one final percentage, such as billed patients divided by total leads. That number hides where the journey fails. Calls about reports, billing or existing appointments should not sit in the same denominator as genuine treatment enquiries. Hospitals should define each stage with clear entry and exit criteria and measure it separately: enquiry to contact, contact to qualified enquiry, qualified enquiry to appointment, and appointment to completed visit. An enquiry is contacted only after a meaningful conversation, not a dial attempt. It is qualified when the treatment need, location, timing and interest are understood. Booking and footfall are separate measures because different operational factors affect them.
Treat a Weak Conversion Rate as a Symptom and Find the Cause
A low call-to-appointment ratio may come from poor intent identification, weak agent engagement, limited service knowledge or short, rushed calls. A low appointment-to-visit ratio may come from missing reminders, unresolved concerns, doctor changes or weak confirmation. Looking only at the final number pushes managers to demand more calls instead of fixing the failing stage. Dashboards should show stage-wise conversion, first-response time, overdue follow-ups, lost reasons and appointment-to-visit performance. Call-quality analysis can then show whether the issue is knowledge, engagement, communication or process compliance. The improvement cycle is simple: find the weak stage, investigate the likely cause, correct the process and measure whether the team follows it.
Prioritise Enquiries by Intent and Record Every Outcome
Not every enquiry needs the same response. A patient asking for an immediate consultation, surgery cost or a specific specialist may need faster attention than a general information request. Intent identification helps separate these enquiries from support calls, while hospital rules set first-response time, the number and spacing of follow-up attempts and escalation. Five calls within two minutes are not meaningful follow-up. When a lead is closed, the record should state why: price, location, doctor availability, timing, a second opinion or lack of interest. Without stages, dispositions and lost reasons, the hospital cannot tell genuine loss of demand from an operational failure.
Building a Measurable Patient Acquisition System
Connecting Marketing, CRM and Hospital Operations
Patient acquisition works best as one connected process. Marketing creates demand, CRM manages the enquiry and hospital operations deliver the appointment and visit. Separate systems and reports make it difficult to see the complete journey.
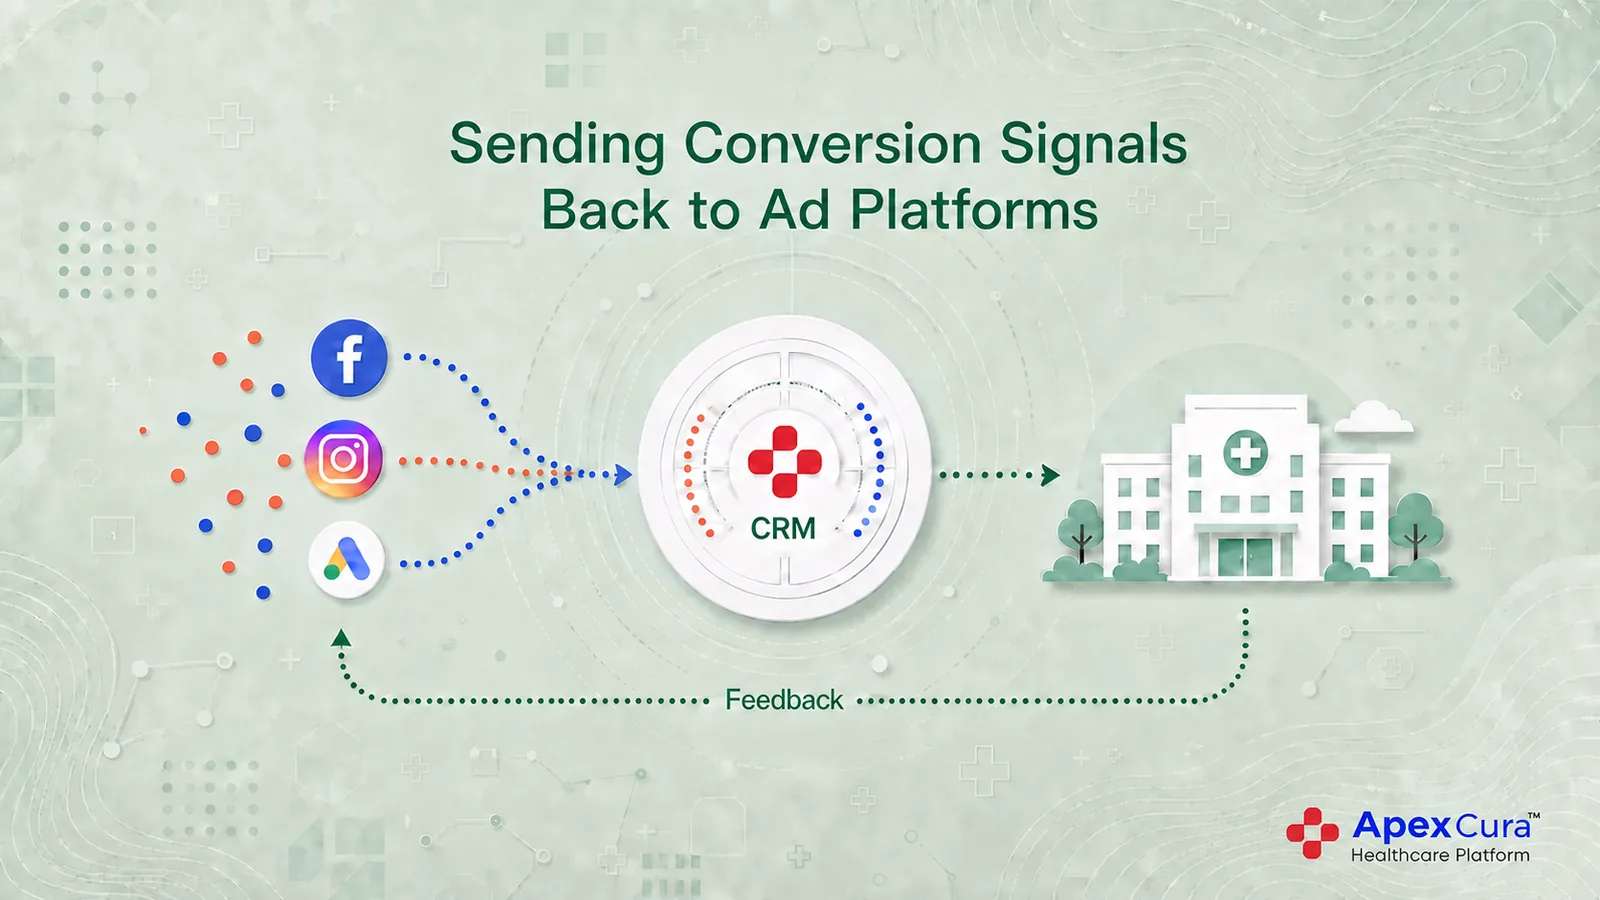
Hospitals should define how source details enter the CRM and how appointment, visit and billing events return from hospital systems. Teams also need shared stage definitions and patient matching rules.
A connected Healthcare CRM for Hospitals can provide the operational link without replacing clinical systems. This helps each team understand its role and gives management one view of patient progress.
Tracking Patient Source, Conversion and Revenue
Lead volume alone does not show acquisition quality. Hospitals should compare each source using appointments, completed OPD visits, procedures, admissions and supported revenue outcomes.
- First-touch source information should remain available as the patient moves through the funnel. Teams should also define how repeat enquiries and existing patients are handled.
- Revenue should come from approved billing data, not assumptions.
- Comparisons may include channel, campaign, speciality, branch and patient requirement.
- These measures help management identify sources that create meaningful hospital outcomes.
- They also reveal when good patient demand is being weakened by slow response or operational gaps after capture.
Scaling Patient Acquisition Across Locations and Specialities
Multi-location hospitals need central visibility with local responsibility. Enquiries should route according to patient preference, speciality availability and branch coverage. Each location needs access to its assigned leads, while central teams monitor response and conversion using common definitions. Some specialities may require dedicated counsellors or longer follow-up cycles.
The CRM should support these differences without creating disconnected processes. Management can compare similar branches and teams, identify capacity gaps and share successful practices. Centralised reporting also shows whether campaigns are generating demand in locations that can serve it. This helps hospital groups scale acquisition while protecting patient continuity and branch-level ownership.
Conclusion
Patient acquisition for hospitals connects marketing demand with operational and clinical outcomes. Hospitals should measure more than calls, forms or booked appointments. They need visibility from the first enquiry to the OPD visit and, where relevant, procedure or admission. Connecting marketing, CRM and hospital systems reveals where patients leave the journey. It also helps teams improve ownership, response and follow-up. Conversion improves when each stage is measured separately and every weak stage is traced to its cause. A measurable acquisition process allows leadership to invest in channels and operations that create better patient and hospital outcomes.